Deep sedation lets you sleep during surgery or invasive procedures. Learn how it differs from general anesthesia, the drugs used, monitoring and risks.
Deep sedation is a medical procedure that consists of inducing an artificial sleep, usually to make another medical procedure, such as surgery or an invasive procedure, more acceptable and pleasant.
Let's find out more about the details.
What is deep sedation
In the field of anesthesiology, deep sedation refers to the medical procedure that induces a state of general relaxation of the patient with artificial sleep, obtained by using one or more sedative agents, which reduce the state of excitement or anxiety until they induce sleep, [1] combined with drugs for analgesia.
Differences between conscious sedation, deep sedation and general anesthesia
Deep sedation means that the patient is asleep but potentially rousable. The patient therefore sleeps and dreams but, if needed, can be woken up with a touch stimulus or a loud call. This is the main difference from the sleep induced during general anesthesia, which is much deeper and from which one cannot be woken up.
In more technical terms, unlike general anesthesia, during which the patient completely loses consciousness, temporarily, deep sedation works by abolishing consciousness in a non-permanent way; the artificially induced state of depressed consciousness can in fact be restored, at least partially, by intense touch or pain stimulation.
The degree of sedation depends on individual susceptibility to drugs
This consideration accounts for each patient's individual sensitivity to the administration of sedative agents: each person responds differently to increasing doses of a drug. For this reason, since the patient's response to treatment is not always predictable, in order to obtain the desired effect it is often advisable to give test doses of the drug to assess the individual response, first passing through conscious sedation and then reaching deep sedation at the desired level, with gradually increasing doses of the drug.
Differences between conscious sedation and deep sedation
In conscious sedation the ability to respond to verbal commands and touch stimuli remains almost unchanged, while in deep sedation the depression of consciousness is more marked, between deep sleep and coma, and active intervention may be required to keep the airway open.
Given the nature of deep sedation, in which there is a state of general relaxation of the patient and deep sleep, it is particularly suitable during operations of a certain length, during which it would be particularly unpleasant for the patient to stay awake the whole time. Typical examples of its use are orthopedic operations on the lower limbs, such as hip or knee replacement with a prosthesis, or operations on the upper limbs.
Indications for deep sedation
Deep sedation, as mentioned, induces deep sleep so that the patient does not perceive noises, conversations or movements in the surrounding environment. It is particularly suitable for those procedures, such as some surgeries, in which general anesthesia is not needed but anesthesia can be performed locally, that is, with spinal anesthesia or a nerve block. In this case the absence of pain during surgery is achieved with local anesthetics, but it is advisable for the patient to sleep to avoid discomfort, such as long operating times or intraoperative positions that are difficult to hold completely still.
Deep sedation in major surgery
Deep sedation is used even for major surgery, such as:
- Non-demolitive reconstructive cosmetic surgery operations, such as breast augmentation, liposuction and abdominoplasty, which do not require full general anesthesia.
- Major orthopedic operations, such as the reduction of dislocations or bone fractures, hip or knee replacement with a prosthesis, or operations on the upper limbs.
- Vascular surgery operations on the upper or lower limbs.
- Complex or extensive dental procedures, such as multiple tooth extractions, oral surgery or periodontal treatments.
- Urological operations, such as cystoscopy or lithotripsy.
Deep sedation is also used successfully when endoscopic maneuvers are performed for exploratory or interventional purposes, for example during gastroscopy with ERCP, operative or interventional bronchoscopy, or colonoscopy. [6]
In all these cases anesthesia is generally local or loco-regional, that is, by placing local anesthetic drugs near the nerve structures that must not perceive pain
Deep sedation combined with other anesthetic techniques
Sedation, light or deep, as in the case of surgery, is often combined with other anesthetic techniques:
- with spinal anesthesia
- for epidural anesthesia
- with a peripheral nerve block (usually for the upper limbs)
Overview of the differences between conscious sedation, deep sedation and general anesthesia
| Conscious sedation | Deep sedation | General anesthesia | |
|---|---|---|---|
| Depression of consciousness | Minimal | Medium-high | Marked |
| Wakefulness | Awake: the patient is cooperative | The patient wakes up after repeated touch or painful stimulation | Unconscious: the patient does not wake up even after painful stimulation |
| Route of administration of sedative agents | Inhalation Intravenous Enteral | Inhalation or intravenous | Often intravenous |
| Total recovery time | Fast, within a few hours | Intermediate | Not very fast, possibly several hours |
| Spontaneous breathing | Adequate | Not always adequate: mechanical assistance may be needed | Not adequate: ventilation required |
| Cardiovascular function | Normal | Generally normal | Altered |
Preoperative assessment for deep sedation
Consultation with the anesthesiologist for deep sedation
The decision to give the patient deep sedation rests primarily with the Anesthesiologist-Intensivist, who is the only specialist authorized to perform it, except in emergency-urgency situations, when it can also be performed by non-anesthesiologist doctors for specific needs.

If deep sedation is requested, an anesthesia consultation must be carried out, during which the patient is properly informed and gives their consent to the procedure.
The consultation with the specialist before deep sedation
Before the procedure is performed, in fact, the patient needs to have an in-depth interview with the anesthesiologist, in order to review the patient's clinical history and detect any possible contraindications to the procedure.
Generally, after collecting all the medical history data concerning the patient's overall health and the list of medications taken, some routine blood chemistry tests may be requested, possibly together with a chemical-physical and morphological urine test. The preoperative consultation then ends with the patient signing the informed consent form.
The blood tests often requested are:
- Complete blood count;
- Non-specific markers of inflammation: ESR and CRP;
- Liver function panel;
- Kidney function markers;
- Coagulation panel.
The physical examination and the medical history are two essential steps for the correct preoperative assessment of the patient who is about to receive deep sedation, because these investigations may reveal any coagulation deficits or vital signs suggestive of disease, such as hypertension.
It is good practice for the patient to arrive for the procedure completely fasting for at least 7-8 hours (with the related restriction of liquids in the previous 3-4 hours), and accompanied by someone they know for the return home.
The drugs used for deep sedation
The drugs used to obtain deep sedation do not belong to a single category and can produce different effects in terms of analgesia, sedation and loco-regional anesthesia. It is therefore important to be able to predict the interactions that can arise when giving a combination of different drugs.
The classes of drugs most commonly used in deep sedation are:
Benzodiazepines
Benzodiazepines are psychoactive drugs with anxiolytic and sedative-hypnotic properties: the most commonly used are those with a short half-life and a fairly rapid onset of action.
The purpose of using benzodiazepines is to induce sleep. The drugs belonging to this category are midazolam, diazepam, triazolam and loprazolam. They can be given by mouth or intravenously, but also intranasally in children or in less cooperative patients, to achieve initial relaxation and then, if needed, proceed with another technique or another drug.
Sedative and/or anesthetic drugs
Sedative or anesthetic drugs have a final effect that depends on the dose given: since they can lead to temporary loss of consciousness, decisions on their use must necessarily be left to an Anesthesiologist-Intensivist. This category includes barbiturates, propofol, halogenated anesthetic gases and many others.
Techniques for performing deep sedation
Deep sedation is generally induced intravenously. In rare cases it can be induced using other routes of administration, namely the enteral or the inhalation route.
Intravenous conscious sedation technique
The intravenous deep sedation technique is the one that offers the highest margins of safety and reliability for the success of the procedure, and generally involves giving a combination of drugs.
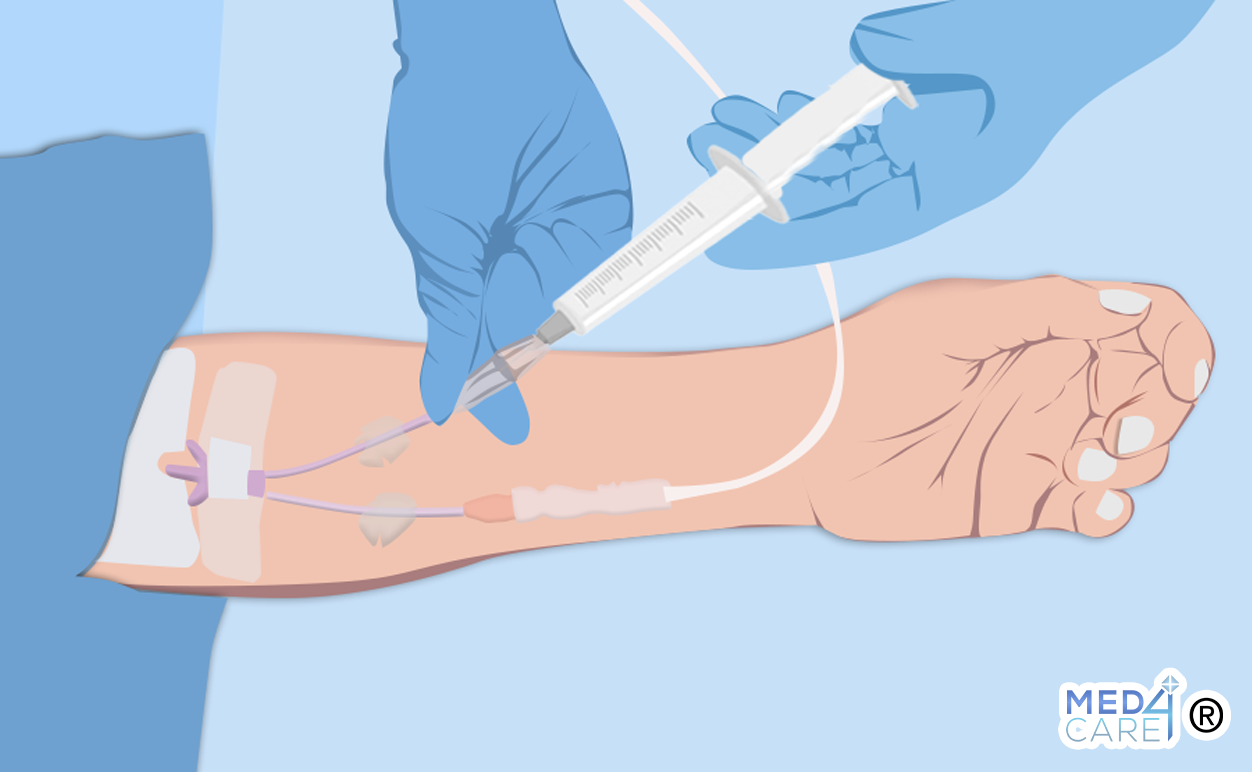
Before performing the procedure, it is necessary to carefully review the patient's clinical history during the anesthesia consultation.
The anesthesiologist will be present throughout the procedure.
The drugs used will generally be given by intravenous injection as boluses, or as a continuous infusion. The most widely used drug is propofol, a whitish general anesthetic/sedative, which causes a sensation of pain or burning at the first injection. This disappears during the procedure and/or as the patient falls asleep.
In all cases of intravenous conscious sedation, the presence of devices for instrumental monitoring of cardio-respiratory function and of a venous access for catheterization must always be ensured.
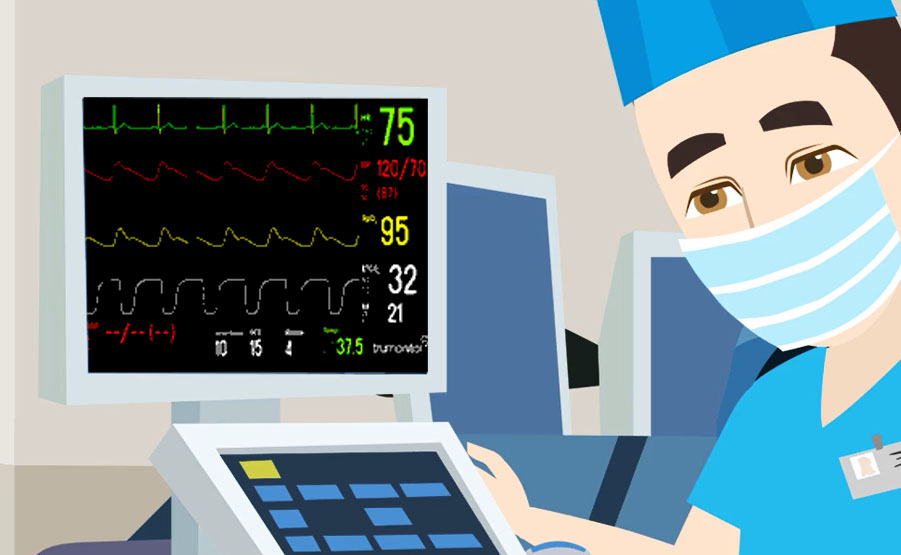
Monitoring of vital signs during deep sedation
During deep sedation the patient's main vital signs are monitored, just as during general anesthesia. Heart rate, blood pressure, respiratory rate and tissue oxygen saturation are checked.
Recovery from deep sedation
Once the procedure is over, the patient must gradually recover consciousness; usually a recovery room is specially set up right next to the operating room, while in other cases the patient recovers directly in the operating room.
It is the specific duty of the anesthesiologist to wait for the patient's complete recovery, constantly monitoring their vital signs, including heart rate, blood pressure and respiratory rate.
The patient MUST be accompanied home by a family member or someone they know, because some side effects, such as drowsiness and slowed reflexes, can last for the whole day.
Risks and complications of deep sedation
Risks during the deep sedation procedure
Sedation induces a depression of consciousness and there is wide individual variability in the response to drugs. So it often happens that the right dose for one patient is excessive for another, and vice versa. Thus the dose given may turn out to be excessive for the individual patient, and there may be a loss of breathing effectiveness, apnea, or an excessive reduction in airway control due to the lack of reflexes. In this case the anesthesiologist will have to assist breathing until the patient recovers it on their own, naturally. It is also possible to use antidotes to the drugs used, such as flumazenil as an antidote to benzodiazepines.
The side effects that could appear after a deep sedation procedure are:
- Temporary change in sensation, with paresthesia or hypoesthesia, usually related to the local anesthesia given during the procedure;
- Hypoxia/Hypercapnia, if breathing is reduced as a result of an excessive dose of sedatives;
- Muscle asthenia;
- Lowering of blood pressure due to the sedatives reducing overall sympathetic tone;
- Cardiac conduction disorders due to an overdose of sedative and/or anesthetic drugs;
- Visual hallucinations due to the side effects of the drugs used, particularly with ketamine.
Conclusions
Deep sedation is a procedure with excellent safety margins that is widely used in anesthesia, in particular for performing surgery with local anesthesia and sedation rather than full general anesthesia, which can cause greater discomfort and risks.
Deep sedation can be induced using a combination of drugs and is given parenterally. It has now become a routine procedure for surgeries that do not require general anesthesia and is well received by patients and healthcare workers.

Dr. Marco De Nardin
Medical Doctor, Specialist in Anesthesiology, Intensive Care and Pain Management
Dr. Marco De Nardin is a physician specializing in Anesthesiology, Intensive Care, and Pain Management. He completed his medical degree and specialty training in Italy, where he continues to practice at his private clinics in Mestre (Venice) and Milan. With extensive clinical experience spanning operating rooms, intensive care units, and pain management clinics, Dr. De Nardin brings a unique perspective that bridges acute-care medicine with chronic disease management. His clinical practice focuses on regional anesthesia, ozone therapy, intravenous infusion therapy, and integrative approaches to pain treatment. He is the founder of Med4Care, a medical information platform delivering evidence-based, physician-reviewed health content. Every article published under his name reflects his commitment to making complex medical topics accessible to patients without compromising scientific rigor.